Best Med Spa Software: Pricing, Memberships and Practice Fit
The best med spa software depends on who runs your front desk, how you document treatment and what you promise your members. A solo injector needs an affordable system they can run between appointments. A growing practice needs the same patient, payment and treatment records to stay accurate across a team. This guide helps you shortlist platforms, compare the full bill and see what each system needs to prove before you switch.
Editorial details
Your first shortlist
Where would we start?
Aesthetic Record for a cost-conscious solo injector; Mangomint and Boulevard for small teams comparing booking, checkout and memberships; PatientNow for broader clinical and operational needs; Zenoti for a multi-location evaluation. These are starting shortlists, with alternatives below.
What does it cost?
Published starting examples include $15 per user/month plus $399 setup at Aesthetic Record, $120 per location + $10 per user/month at Mangomint, and $199/month for up to three bookable professionals on Boulevard’s Medspa Essentials plan. Those prices buy different things.
What changes the decision?
Test your actual membership, treatment record and checkout. Then compare processing, add-ons, contract terms and the cost of moving records. A low subscription can still produce a higher total bill.
How was this compared?
Darryl’s past operating experience with Aesthetic Record and PatientNow informs the questions in this guide. Current vendor documentation and prices checked October 7, 2026. These are editorial shortlists, not fresh hands-on ratings. No vendor paid for placement.
Choose a shortlist for your practice
Start with two or three systems. Give each the same staff count, service menu, membership promise and sample workflow. That makes the conversation much more useful than collecting ten unrelated demos.
| Your situation | Start by comparing | What should decide it |
|---|---|---|
| Solo injector or one clinical provider | Aesthetic Record, then Mangomint | First-year cost, fast treatment documentation, photo records and the amount of administration you can handle alone. |
| One or two providers plus a receptionist | Mangomint and Boulevard; compare Aesthetic Record if clinical documentation and low licensing cost lead | Count every paid user or bookable calendar correctly. Test handoffs from intake to provider to checkout. |
| Established or growing clinical practice | PatientNow, alongside Aesthetic Record | Clinical workflow, inventory, lead follow-up, role permissions and reporting without duplicate entry. |
| Multiple locations or a group preparing to expand | Zenoti and Boulevard’s enterprise offering | Location permissions, shared patients, cross-location redemption, consolidated reporting and rollout support. |
| Memberships are central to the offer | Mangomint, Boulevard and Zenoti make a useful initial comparison | Prove the exact dollar-credit or treatment-benefit rules. Recurring billing alone does not establish that the plan will work. |
These recommendations reflect the published scope and pricing structure, rather than an award for usability. A well-configured system outside your first shortlist may be the better fit. If a platform fails a requirement you need every day, move on before negotiating its price.
For a new practice, separate essentials from expansion features. Booking, consent, treatment records, payments and usable exports come first. An advanced campaign builder becomes valuable when somebody has the time, permission and process to run the campaigns. Our startup budget guide helps put software into the wider launch budget.
Compare platforms and current pricing
The table uses US pricing observed on October 7, 2026. Subscriptions exclude processing, taxes, hardware and unlisted implementation or optional services. “Confirm quote” means we could not establish a current public US amount from the pricing view reviewed; it is not an estimate of zero or a judgment about value.
| Platform | Published subscription reference | Useful reason to shortlist it |
|---|---|---|
| Aesthetic Record | Essentials $15/user/month; Accelerator $19/user/month. $399 startup fee. | Aesthetics-focused clinical workflows with a low per-user starting price. |
| Mangomint | $120/location/month + $10/user/month. Optional services extra. | Booking, checkout, forms and memberships with a straightforward base formula. |
| Boulevard | Medspa Aesthetics Essentials $199/month, up to 3 bookable professionals. Regular monthly Premier $455, Prestige $520 per location; promotions displayed separately. | A small-team Medspa plan and larger tiers with different communication allowances. |
| PatientNow | Quote-based Standard, Amplify and Catalyst plans. | A clinical practice that also needs lead management, photography and growth tools. |
| Zenoti | Configured quote; AI workforce has separate pricing. | Teams evaluating group operations, location control and membership configuration. |
Price sources: Aesthetic Record, Mangomint, Boulevard, PatientNow and Zenoti.
A user is not always a provider. Receptionists and managers can count as paid users even if they never treat anyone. Other systems charge by bookable calendar. Give sales a list of everyone who needs a login, every provider who takes bookings and every location. Ask for a written seat calculation.
Aesthetic Record
Our shortlist use: a solo injector or smaller aesthetics practice that wants clinical documentation without a large base subscription.
Its published plans combine treatment records and photographs with inventory, memberships, packages and a patient wallet. Count every staff login, including reception. Essentials includes 2 GB storage per user, plus 250 SMS and 300 emails per user/month. Accelerator raises those allowances to 4 GB, 400 SMS and 600 emails. Prescribing, payment services and some integrations cost extra. Plan details.
The two-way inbox costs $5/month and requires Accelerator. SMS allowances count message segments, so a longer text may use several credits. Confirm POS fees and usage top-ups in the quote. During the demo, send an incoming reply with the staff app closed and phone locked: can the intended person notice and handle it promptly? Inbox and SMS billing.
The patient portal documentation distinguishes wallet dollars from banked products or services. That is useful for a practice selling both credit memberships and prepaid treatment benefits. Wallet documentation.
Prove before choosing: record a fictional injectable visit, take it through review and sign-off, redeem wallet credit, then reconcile the stock used and the balance left. If your follow-up depends on a separate CRM, include that integration and staff time in the decision.
Mangomint
Our shortlist use: a solo provider or small team prioritizing booking, client communication, checkout and repeat visits alongside charting.
Its current base price includes forms and charting; phone, marketing and payroll are optional services. Confirm which messages fall within your selected package. An older review’s tier price may describe a previous pricing structure. Current pricing.
Clinical forms support notes, image markup and review/approval assignments. Mangomint says practices should contact support to enable its HIPAA configuration and sign a BAA. Medical-spa documentation.
Prove before choosing: have the provider finish the chart while the receptionist checks out a member. Confirm the approval process suits your supervising clinician, and that your inventory records capture the product detail you need. A smooth booking flow and a suitable medical record are separate checks.
Boulevard
Our shortlist use: a small team comparing patient-facing booking and checkout, with a path to larger location operations.
Select Medspa on the pricing page. The salon plans are a different comparison. We verified the monthly Medspa view in the browser: Essentials includes up to three bookable professionals, forms/charting and photo tools. Larger tiers change limits and included communications. Annual equivalents and promotional prices also appear; compare the renewal amount, not just today’s promotion. Pricing selector.
Its documentation covers membership billing and service vouchers. Those give you specific functions to test when designing included-treatment plans. Billing documentation and vouchers.
Prove before choosing: separate money credited to a member from a service voucher, then process a partial redemption and a cancellation. Get the exact clinical, payment and location configuration listed on your order form.
PatientNow
Our shortlist use: a clinical practice comparing patient records, photography, lead handling and marketing in a broader operating system.
The current Standard plan lists EMR, booking, patient portal, lead management, photographs, memberships and reporting. Amplify and Catalyst expand the scope. Prices are tailored, and several listed functions depend on the practice setup or an add-on. Ask which exact edition and integrations are being demonstrated. Current packages.
Prove before choosing: turn a fictional inquiry into a booked consultation, treatment plan and completed visit. Then follow its photos, payment and follow-up task. This shows whether the promised consolidation actually replaces your existing subscriptions. Include the cost of any separate marketing service, migration work and training in the written proposal.
Zenoti
Our shortlist use: a multi-location practice or a team preparing for growth that wants to test centralized control and local operations together.
Zenoti markets its med spa platform across practice sizes; it is not restricted to large groups. Its current pricing page requires a configured quote and separates AI-workforce pricing.
The membership configuration documentation is especially useful: service credits may be released with each payment or all at once, and the system includes redemption timing settings.
Prove before choosing: buy a membership at one location and redeem it at another. Check the patient view, staff permissions, commissions and location reports. A solo practice can evaluate it too, but should require a clear reason for any extra implementation effort or cost over a simpler configuration.
What med spa software really costs
Use two figures: the cash needed to get started and the recurring cost of running your actual configuration. A yearly total helps compare contracts, but it can hide a large bill due before your first patient arrives.
Compare a defined team, not a headline price
For a fictional one-location team of two providers and one receptionist, the following are subscription illustrations, not equivalent packages or final quotes:
| Configuration | Subscription calculation | First-year subscription and stated startup fee |
|---|---|---|
| Aesthetic Record Essentials, 3 paid users | 3 × $15 = $45/month | $939: $540 subscription + $399 startup |
| Mangomint, 3 paid users | $120 + 3 × $10 = $150/month | $1,800 subscription |
| Boulevard Medspa Essentials, 2 bookable professionals | $199/month; within the published 3-professional limit | $2,388 subscription |
The prices come from the linked vendor schedules above. Each illustration uses monthly billing for 12 months, assumes the same price throughout and excludes processing, optional tools, taxes and implementation costs beyond AR’s stated startup fee. Confirm the receptionist’s permitted access and any non-bookable-user limits with Boulevard. The lowest figure is not a claim that the packages do the same job.
Add the costs the demo leaves outside the slide
| Cost to put in your comparison | The question that gets a useful answer |
|---|---|
| Setup and migration | Does the fee cover demographics only, or photos, charts, forms, appointments and balances? Who fixes a failed import? |
| Clinical requirements | Which plan includes chart review, e-prescribing, photo storage, audit history and the permissions your clinicians need? |
| Communication | Which reminders are included? Are two-way texts, campaigns, phone lines and AI minutes separate? What happens above the allowance? |
| Payments and hardware | What are the rates for in-person, online, saved-card and recurring payments? Add terminals, monthly fees and chargebacks. |
| Your team’s time | Who builds templates, services, memberships and automation? How many paid training and transition hours should you budget? |
| Exit costs | What costs money to export, how long does it take, and will you need paid read-only access after leaving? |
One useful comparison is new spending minus subscriptions you can actually cancel. Keep a CRM cost in the budget until you have proved that the replacement can handle its forms, attribution, follow-up and reporting. A feature with a similar name may serve a different purpose.
When processing outweighs the subscription
Consider two fictional offers with the same $0.10 transaction fee. Offer A costs $150/month plus 2.9%; Offer B costs $300/month plus 2.5%. At $20,000 in monthly card sales and 100 transactions, A totals $740 and B $810. At $60,000 and 300 transactions, A totals $1,920 and B $1,830. The higher subscription becomes cheaper as the processing difference grows.
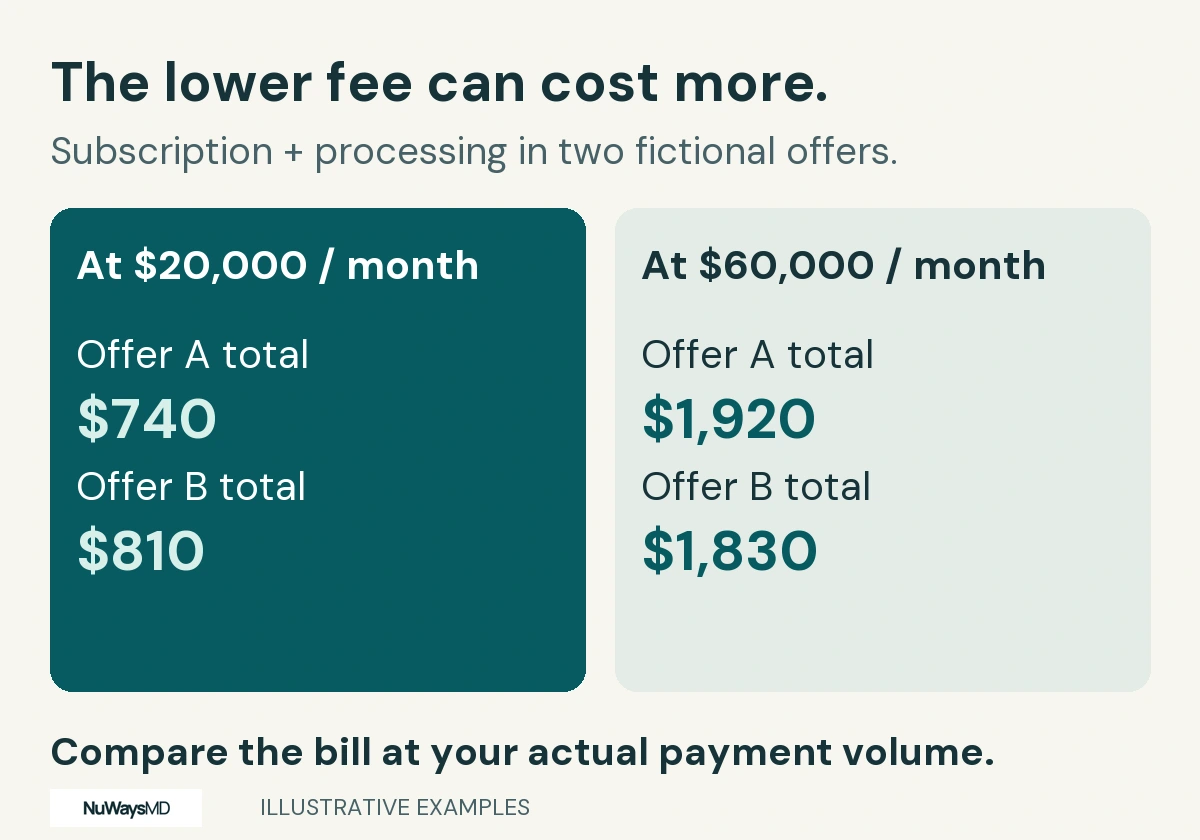
With those assumptions, the $150 subscription difference equals the 0.4-percentage-point processing difference at $37,500 a month. Real offers may also differ in per-transaction charges, card types, financing, refund fees, deposits and recurring-billing rates. Use your actual payment mix. This is a comparison method, not a vendor rate quote.
Why memberships change this: a practice may collect payments online or through saved cards even when treatment happens in person. Ask for the rate applied to those collections. A low terminal rate tells you little about the cost of charging hundreds of members automatically.
Build your software cost estimate
Use the existing calculator below to compare recurring costs and transition work. Its saved worksheet is a separate planning tool; requesting the blank email scorecard does not send your business figures to a vendor.
Your software costs and demo checklist
Use the example to understand the calculation, then start with your own figures. All money is in US dollars.
Calculate to see the breakdown.
Keep the figures and the next steps together
Save this editable worksheet, track the five preparation steps and download a copy. Return through your private practice workspace. No email delivery, marketing enrollment or vendor introduction is included.
Test memberships, packages and unused balances
For a membership-led practice, this can decide the shortlist. A system can successfully charge a card and still make the receptionist manually track what the patient is owed. Build the promise from your membership pricing plan inside the software before selling it.
Money and treatment benefits need different records
In a fictional $149 monthly beauty bank, three successful payments create $447 of paid credit. If an eligible $300 treatment receives a 10% member discount, the charge is $270 and $177 remains. The receipt should show the discount, credit used and remaining balance clearly.
In a fictional $189 monthly included-treatment plan, three successful payments collect $567 and release the agreed treatment benefit. That is a treatment entitlement. It should not also leave $567 available to spend again unless your offer deliberately includes both benefits and has been priced accordingly.

Run these five situations during the demo
| Situation | What a useful demonstration proves |
|---|---|
| Member joins, then returns after three payments | The correct dollars or service benefits become available at the promised time. A discounted treatment reduces the correct balance. |
| Next payment fails | Staff can see the failure, know who follows up and understand which existing benefits remain available. Future benefits follow the agreement’s rules. |
| Member pauses or cancels | Future billing stops as agreed. Already-paid credit and benefits are handled separately from future charges, with an understandable record. |
| Partial refund or service change | The refund, restored benefit, commission and inventory changes reconcile. Replacing a service does not silently create extra value. |
| Member uses another provider or location | Eligibility, restrictions, provider pay and location reporting follow your rules. The patient sees one understandable balance. |
A software setting is not your cancellation policy. Decide the permitted treatment of paid balances and unused benefits with appropriate advice, then configure and test it. Keeping historical paid credit visible does not mean all future benefits must remain active after cancellation.
What the published documentation already establishes
These examples make the demo more specific; they are not completed NuWays MD tests.
- Mangomint: its membership FAQ describes dollar-balance plans and service plans. It also describes payment retries and a move from past due to unpaid. Ask the demonstrator to show your chosen benefit rules through that sequence.
- Boulevard: its billing guide explains failed-billing visibility and cancellation, while its voucher guide covers service redemption. Test which balance the member sees after each action.
- Zenoti: its configuration guide explains releasing credits with payments or upfront. Use the timing that matches the benefit you sold.
For every platform, export the opening balance, additions, redemptions, refunds and closing balance. Your bookkeeper should be able to follow the movement without reconstructing it from appointment notes. Our service-pricing guide helps connect what is redeemed to the cost of delivering it.
Follow one patient from booking to follow-up
Ask for a synthetic patient, a routine injectable visit, a retail purchase and a later review. Run the journey yourself when sandbox access is available. Watching a practiced demonstrator is useful, but it does not show whether your receptionist can recover from a mistake.
| Step | The practical task | What to notice |
|---|---|---|
| Booking and intake | Choose a service, pay a deposit, complete forms and reschedule | Mobile friction, duplicate profiles, appropriate room/provider availability and how the deposit moves. |
| Clinical record | Document product, lot, treatment details, photos and consent | Retrieval, signatures, review, corrections and who can change a completed record. |
| Inventory | Use part of a product quantity and sell one retail item | Product-specific units, wastage, stock movement, reorder view and permissions. |
| Checkout | Redeem credit, apply an eligible discount, collect the rest | An understandable receipt, correct balance, tax treatment and provider compensation. |
| Follow-up | Schedule a review and assign a callback | The task reaches the right person and remains visible until handled. |
| Management | Review the visit’s payment, outstanding benefit and staff activity | Reports distinguish collected money, delivered services, refunds and unused obligations. |
Clinical workflow: what your team needs to prove
Choose these checks by the services you provide, not how long you have been open. A startup offering medical treatments may need prescribing and supervisory review from day one. An established clinic also needs to preserve the connections its team already relies on. Run the relevant rows with the clinician and front-desk person who will use them.
| Workflow | What to demonstrate | Why it matters |
|---|---|---|
| Charting | Finish a treatment-specific note, record product and lot details, sign it, then correct an error while preserving the original and who changed it. | A flexible form is useful only if the finished record is complete, traceable and easy to retrieve. |
| Oversight and examinations | Show the assessment or good faith exam (GFE), treatment authorization, unsigned-chart queue and reviewer access for medical director or supervising clinician sign-off. Test reassessment reminders and supervisory seat costs. | Staff need to see what is ready and what still needs review. Configure this to your clinical team’s requirements; software does not determine who may treat or when another examination is required. |
| E-prescribing | Use a synthetic patient to demonstrate medication history, pharmacy selection, refill requests and the prescription saved in the chart, without sending a real prescription. Check compound-entry support if your prescribers need it. | Price each prescriber, required verification and renewal. A linked prescribing service may be sufficient; test the handoff and supported pharmacies. |
| Clinical photographs | Capture the same view twice with alignment aids, attach both to the correct visits, compare them and export the originals. Check access and separate marketing consent. | Overlays can help positioning, but lighting and capture technique still matter. An upload button does not prove compatibility with your imaging system. |
| Manufacturer rewards | Demonstrate an eligible reward, its redemption, receipt entry and reimbursement report for the programs you use. | Distinguish a portal shortcut from an integration that exchanges data. Check how rewards interact with your member discounts. |
| Patient financing | Follow approval through a financed or split payment, then a refund and settlement report. Match gross sale, lender fee and net deposit. | A separate financing portal can work, but manual steps and responsibility for reconciliation must be clear. |
| Treatment supplies | Complete a sample service and check product use, configured consumables, waste and stock corrections. Adjust the supplies when the visit differs from the template. | A treatment recipe can save entry, but it needs accurate quantities and exceptions. Start with high-value stock and useful supply tracking rather than tracking every inexpensive item. |
For example, AR documents e-prescribing, a Qualiphy examination workflow and Cherry checkout. Its rewards documentation distinguishes portal access from specific integrations. These are documented capabilities to test in your quoted setup, rather than a completed NuWays MD evaluation.
Already running a clinic? Bring your existing connections
- List your prescribing service, pharmacies, imaging system, rewards programs, financing providers and CRM. Mark which must stay.
- Have each vendor show what transfers automatically, what staff re-enter, which plan enables the connection and its separate fees.
- Rehearse one failed handoff, such as a patient reply or a refund that does not sync. Assign who spots and resolves it before switching.
CRM and automation: follow an inquiry into the patient record without duplicate entry, preserving its source and communication permissions. Confirm who sees an unanswered message or an integration error. A connected app is useful when your team can follow the work through to completion.
Evaluate AI by the work it finishes correctly
AI can help with calls, messages and draft notes. In a demo, give it a rescheduling request, an uncertain answer and a request requiring a human. Check escalation, correction history and the completed task. For clinical notes, the provider must review the output before relying on it. Ask where data goes, which service processes it and what is covered by your agreements. Budget usage overages as well as the subscription.
Score the demo and check the contract
Use pass, needs work or fails for the requirements that matter. Keep an additional unverified label for a claim you have not seen demonstrated. Ten attractive extras should not outvote a failure to retrieve records or account for member credit.
Choose your five must-haves before the demo. For a solo provider, that might be a complete clinical record, mobile booking, simple checkout, affordable total cost and a usable export. A managed team may add review permissions, membership reporting and a reliable integration to its existing CRM.
A 45-minute demo agenda
- First 5 minutes: confirm the exact plan, staff roles and sample membership. Skip the generic company presentation.
- Next 15 minutes: run booking, intake, a treatment record and checkout with the same synthetic patient.
- Next 10 minutes: fail a renewal, redeem part of a balance and cancel future billing.
- Next 10 minutes: show reports, export sample records and inspect the cost proposal.
- Final 5 minutes: list unresolved items, assign an owner and agree on written follow-up. Schedule a second session for any clinical workflow the first demo could not cover.
Get the agreement to match the demonstration
Record the plan name, locations, user types, modules and implementation services. Ask for the minimum term, renewal date, notice window, post-promotion price and any rate-change rights. “Monthly payment” can still be a payment schedule inside an annual commitment.
For payments, confirm whether you must use the integrated processor and what happens to hardware, saved cards and recurring memberships if you leave. For migration, attach the agreed data list and acceptance checks. For support, distinguish onboarding help from ongoing assistance, escalation hours and work billed separately.
Keep evidence of the unresolved items. A helpful salesperson may believe a workflow is possible, while the needed module, configuration or integration is outside your quote. A written answer or a second demo is more useful than a confident verbal assurance.
Switch without losing records or member trust
Start with a small test migration. Moving a contact list proves very little about photos, signed charts, future appointments and unused benefits. The hard part is preserving what each record means and connecting it to the right person.
| Data group | Check before the old account closes |
|---|---|
| Patient records | Correct identity, notes, signatures, attachments, dates and access to amendments or history. |
| Photos and forms | Original image quality, labels, dates, signed documents and links to the right visit. |
| Future appointments | Provider, room, service, deposit, reminders and rescheduling behavior. |
| Money and benefits | Paid credit, gift balances, remaining sessions, membership terms, refunds and next billing dates. |
| Permissions and marketing | Staff access, consent status, unsubscribes and the boundaries of any marketing migration. |
Saved payment cards are a separate project. A processor may be able to transfer payment tokens through an approved process, or patients may need to enter cards again. Get both providers’ written migration approach. A patient-list export does not establish that automatic billing will continue.
Reconcile a varied sample: an active member, a patient with a deposit, a partly used package, a refund and someone with extensive photos. Then compare total balances and record counts before and after the full import. Counts help detect missing records; they do not replace opening the records and checking their content.
Agree on a cutover date and which system sends reminders and collects renewals. Assign one person to reconcile the first billing cycle and another to handle patient questions. Keep access to the old records for the period required by your obligations and migration plan, with its cost agreed in advance.
If the main problem is inconsistent staff follow-up or an unclear booking process, fix that before paying to recreate it elsewhere. Our software and workflow decision guide helps separate a system limitation from a process that needs an owner.
HIPAA, access and ownership of your data
For practices subject to HIPAA, a cloud provider that maintains electronic protected health information generally needs an appropriate business associate agreement, or BAA. HHS also makes clear that it does not certify or endorse particular technology products. A vendor’s compliance statement is one part of evaluating your setup. HHS cloud guidance.
Ask who can view, change and export records; whether staff have separate logins; how access is removed when someone leaves; and whether activity is recorded. Include connected phones, forms, integrations and AI services in the review. Use synthetic information in a sales sandbox.
Get the export formats, cost, turnaround and available access after cancellation in writing. Ask for a sample you can open without the vendor’s software. A contract saying you own your data is helpful, but your practice also needs a practical way to retrieve and use it. State-specific medical-record, privacy and retention requirements may apply separately; have the appropriate professional review your obligations.
Frequently asked questions
What is the best med spa software for a solo injector?
We would start with Aesthetic Record for its low per-user price and aesthetics-focused workflow, then compare Mangomint if booking, checkout and repeat-visit administration are central. Test the completed clinical record, not just the appointment calendar. A solo provider should also budget setup, prescribing if needed, storage, messages and payment processing.
Which platform should a one- or two-person team compare first?
Mangomint and Boulevard make a useful pair for booking, memberships and checkout; Aesthetic Record is a relevant lower-base-cost clinical alternative. Count administrative logins separately from bookable providers. The pricing table explains why the same small team can be billed differently by each system.
How much should a small med spa budget for software?
Start with a written configuration rather than an industry average. In our fictional two-provider-plus-receptionist example, three published configurations range from $939 to $2,388 for first-year subscriptions and the one stated startup fee. That is a limited comparison, not a market range or an all-in budget. Add the modules, payment costs, hardware, migration and training your practice needs.
Is an EMR different from booking software or a CRM?
Yes. Booking software manages appointment availability; an EMR holds the clinical record; a CRM manages inquiries and follow-up. One platform may cover all three, but the depth differs. Test each role with a real workflow and include the cost of anything you need to keep separately.
Which software is best for beauty-bank memberships?
Shortlist systems that distinguish dollars from service benefits and can report unused balances. Mangomint’s public documentation explicitly describes account-balance memberships; AR documents a wallet with dollars and banked products or services. Other platforms may also fit. Use the five membership tests above before selecting one for your particular rules.
Can I keep my current payment processor?
It depends on the platform and functions you need. Ask whether outside processing is permitted and which features depend on the integrated processor, such as online deposits or recurring billing. Compare the total cost and workflow of both arrangements, including reconciliation work.
Is annual billing a better deal?
It can reduce the subscription, but only if the system fits and you can commit comfortably. Confirm the total due, term, cancellation rights and renewal price. A modest saving can be poor value if the team has not yet proved the essential workflows or the migration.
Have you tested every platform hands-on?
No. Darryl previously used Aesthetic Record and PatientNow to operate the former practice and attended Boulevard and Zenoti demos. This edition checks current prices and features against public documentation; it is not a fresh hands-on comparison of all five. Historical experience and vendor demonstrations are distinct from testing the current product.
Do vendors pay to appear in this comparison?
No vendor paid for placement in this edition. Any future affiliate or sponsored relationship will be disclosed where relevant. Commercial support does not establish that a workflow works; the evidence and limitations still need to be shown.
Sources and editorial notes
Sources and US prices checked October 7, 2026. Prepared by Darryl H., Founder & Editor and former med spa co-owner and practice manager. This is business buying guidance based on documentation, with original comparison methods and clearly fictional financial examples. It is not a security certification, legal review or completed hands-on test of each product.
Pricing and platform scope
- Aesthetic Record: plans and allowances and patient wallet documentation. Supports licensing, setup and the distinction between wallet dollars and banked items.
- Mangomint: pricing, clinical forms and medical-spa setup. Current base formula, optional services and documented charting/BAA configuration.
- Boulevard: pricing. Medspa and monthly selectors inspected in the browser. Regular prices are separated from displayed promotions and annual equivalents.
- PatientNow: current pricing and plan scope. Tailored quotes and feature-availability qualifications, rather than old package names or expired promotions.
- Zenoti: pricing and med spa scope. Configured pricing and the published operational positioning.
Membership operations, clinical workflow and privacy
- Membership behavior: Mangomint FAQ, Boulevard billing and vouchers, and Zenoti configuration. These establish documented functions, not success in an unperformed test.
- Clinical workflow: AR’s e-prescribing, Qualiphy, checkout and rewards instructions support the named examples. The checklist is our evaluation method. Examination, prescribing and supervision requirements depend on the practice’s clinicians, services and jurisdiction.
- Communications: AR’s inbox setup and segment billing support the plan restriction, fee and allowance explanation. Mobile alert behavior is a test question, not a claim that the current app lacks notifications.
- Privacy: HHS cloud-computing guidance. Compliance depends on the practice, agreements and configuration as well as the software.
How we made the shortlist: relevance to US med spa workflows, current primary-source information, a range of pricing structures and different practice sizes. The order is not a paid ranking. Missing price or workflow evidence is labeled rather than filled with assumptions. Public documentation cannot establish ease of use, implementation quality, negotiated rates or support performance. Quotes and plan features can change after this check.
Original material: NuWays MD created the processing-cost illustration, membership-ledger examples and printable demo scorecard. They are teaching tools, not vendor tests or accounting advice. The software calculator is a planning aid; check the current quote before committing.